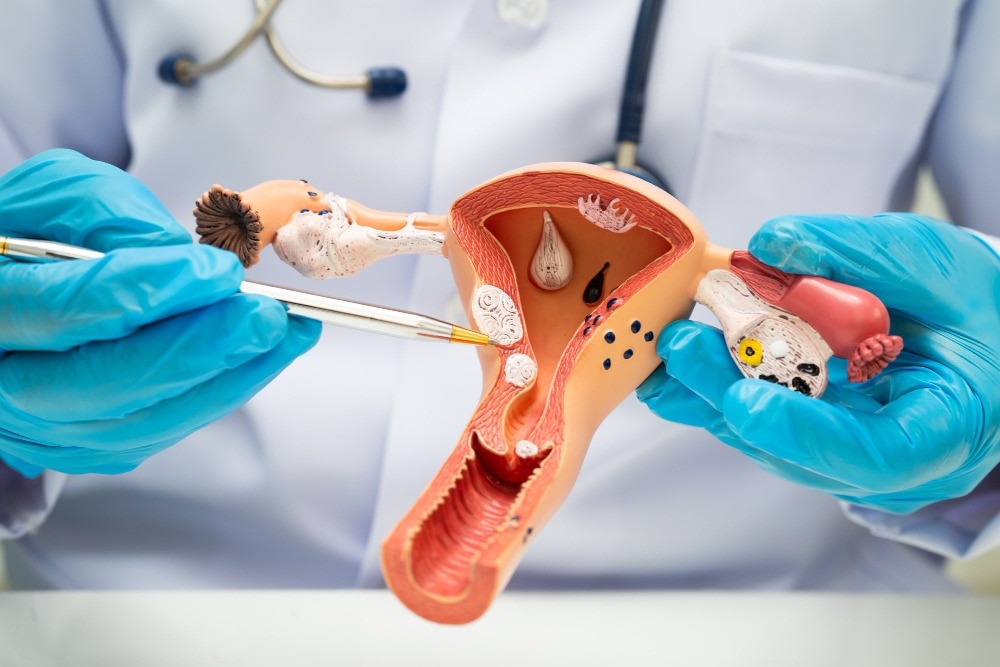
A feeling of vaginal looseness can follow childbirth, pelvic-floor dysfunction, prolapse, hormonal changes or changes in sexual sensation, and each cause calls for a different response. By the end, you will know which symptoms warrant assessment, how vaginoplasty, perineoplasty, laser and radiofrequency treatments differ, and what to ask before choosing treatment.
Key takeaways
- Seek assessment for bulging, pressure, pain, or bladder and bowel symptoms.
- Identify childbirth injury, prolapse, pelvic-floor weakness, or hormonal changes first.
- Compare physiotherapy, surgery, laser, and radiofrequency by risks and expected benefits.
- Ask about evidence, recovery, complications, alternatives, and follow-up before consenting.
What vaginal laxity can mean—and which symptoms need assessment
A feeling of looseness is not, by itself, a diagnosis. Vaginal laxity can reflect normal anatomy, changed sexual sensation, pelvic-floor weakness, childbirth-related perineal injury, prolapse, or hormonal tissue changes. A stable sensation without pain, pressure, bulging, or bladder or bowel symptoms may not indicate a structural problem.
Clues that change the decision include:
- New or worsening looseness after childbirth, pelvic surgery, menopause, or breastfeeding
- Pelvic pressure, a vaginal bulge, or tissue felt at or beyond the vaginal opening
- Urinary leakage, difficulty starting urination, or trouble emptying the bladder
- Constipation or difficulty emptying the bowel
- Pain during penetration, burning, dryness, itching, unusual discharge, or fragile skin
- Reduced sensation that causes distress or interferes with sexual function
| Situation | Clues | Why assessment matters |
|---|---|---|
| Normal variation | Long-standing feeling of looseness without pain, pressure, bulging, or bladder and bowel changes | A tightening procedure may offer little benefit |
| Pelvic-floor dysfunction | Weak contraction, poor relaxation, leakage, or reduced support | Pelvic-floor physiotherapy may be more appropriate |
| Pelvic-organ prolapse | Pelvic pressure, bulge, urinary retention, constipation, or incomplete bowel emptying | Treatment may involve therapy, a pessary, or reconstructive surgery |
| Hormonal, infectious, or skin condition | Dryness, burning, painful sex, itching, discharge, or tissue fragility | Narrowing the vagina could worsen symptoms |
A clinician needs your childbirth, menopause or breastfeeding, sexual-pain, urinary, bowel, medication, and future-pregnancy history. Examination can assess the vulva, vaginal walls, pelvic-floor contraction and relaxation, and prolapse before any procedure is considered.
Find the underlying cause before choosing a tightening procedure
A clinician determines the cause through a targeted history, pelvic examination and pelvic-floor evaluation—not by vaginal diameter alone. Ask about childbirth-related pelvic-floor injury, tears or episiotomy, pressure, a vaginal bulge, urinary leakage or retention, constipation, painful sex, dryness, itching, discharge, breastfeeding or menopause, previous pelvic surgery, medicines and future pregnancy plans.
During the pelvic examination, the clinician inspects the vulva and vaginal walls, checks scars, skin changes, tenderness and discharge, and asks you to contract and relax the pelvic-floor muscles. They assess pelvic organ prolapse while you bear down, sometimes using the Pelvic Organ Prolapse Quantification (POP-Q) system.
A vaginal swab can investigate infection; a skin biopsy may be needed for an unexplained lesion.
| Cause | Findings that point towards it | Usual next step |
|---|---|---|
| Childbirth-related pelvic-floor injury | Scar, widened perineum, weakness or pain after a tear or episiotomy | Physiotherapy or targeted repair |
| Pelvic organ prolapse | Pressure, bulge, incomplete bladder or bowel emptying | Physiotherapy, pessary or prolapse repair |
| Infection | New discharge, odour, itching, burning or tenderness | Swab-directed treatment |
| Hormonal change | Dryness, burning and fragile tissue during menopause or breastfeeding | Hormonal or non-hormonal dryness treatment |
| Skin disease | Fissures, whitening, rash or persistent itching | Gynaecological or dermatological treatment |
| Pelvic-floor dysfunction | Muscles that cannot contract, relax or coordinate properly | Supervised pelvic-floor therapy |
A tightening procedure can miss the problem when sexual symptoms arise from pain, dryness, medication or reduced arousal rather than excess tissue. Treat the documented cause first.
How vaginoplasty, perineoplasty, laser and radiofrequency differ
A narrower vaginal canal, a damaged perineum, vaginal dryness and pelvic-floor weakness are different problems. The procedure must match the structure involved; tightening tissue without correcting the defect can leave symptoms unchanged or cause painful narrowing.
| Option | What it targets | When it is the wrong first choice |
|---|---|---|
| Vaginoplasty | Reconstructs or narrows part of the vaginal canal, often for a documented structural problem | A cosmetic measurement is the only concern, or prolapse, pelvic-floor dysfunction or painful sex has not been assessed |
| Perineoplasty or perineorrhaphy | Repairs the perineal body and vaginal opening after childbirth injury, scarring or separation | The main problem is deeper prolapse, urinary leakage, dryness or a normal anatomical variation |
| Laser vaginal treatment | Uses thermal energy on superficial vaginal tissue; it is marketed for tightening or dryness | You need established prolapse or incontinence treatment, or you have pain, infection, skin disease or unexplained bleeding |
| Radiofrequency | Heats tissue to promote a temporary tightening sensation or tissue change | You need repair of a perineal defect or prolapse, or the diagnosis is uncertain |
Laser and radiofrequency devices are not equivalent to reconstructive surgery or pelvic-floor physiotherapy. The FDA has not established their safety or effectiveness for cosmetic vaginal uses and has reported burns, scarring, painful intercourse and chronic pain.
A tightening operation does not reliably prevent recurrent prolapse or urinary leakage. If you may become pregnant, discuss timing before treatment: pregnancy and vaginal birth can stretch a repair, while scarring or narrowing can create new problems.
Compare pelvic-floor physiotherapy with surgery and energy-based treatment
Supervised pelvic-floor muscle training is usually the lowest-risk starting point when weakness, poor coordination or stress urinary leakage is present. It is not a cosmetic vaginal-tightening procedure, and it works best when pelvic-floor physiotherapy confirms that you can contract and relax the correct muscles.
| Option | Effectiveness | Risks | Recovery |
|---|---|---|---|
| Pelvic-floor physiotherapy | Helps selected pelvic-floor dysfunction, especially stress urinary incontinence; it will not repair a major tear or prolapse. | Incorrect exercises can worsen pelvic pain or muscle spasm. | No surgical recovery; improvement requires regular practice and review. |
| Reconstructive surgery | Can repair documented prolapse, childbirth-related defects or perineal separation, but does not reliably prevent recurrent prolapse or urinary leakage. | Bleeding, infection, wound problems, altered sensation, recurrence, reoperation and dyspareunia; over-tightening can cause painful penetration or difficult examination. | Requires wound healing, activity restrictions and follow-up. |
| Laser treatment | Evidence does not establish it as equivalent to prolapse or incontinence treatment. | The FDA has reported burns, scarring, pain during intercourse and chronic pain after energy-based vaginal procedures. | Recovery varies, but injury can prolong pain and require treatment. |
| Radiofrequency vaginal treatment | Claimed tightening or tissue effects are not established substitutes for treating an anatomical defect. | Possible burns, scarring, pain and uncertain long-term benefit. | Usually marketed as shorter recovery than surgery, but symptoms can persist or worsen. |
Choose treatment based on examination findings, not laxity alone. Pressure, a vaginal bulge, urinary retention, bowel-emptying difficulty or persistent pain warrants assessment before any tightening procedure.
Questions to ask before consenting to treatment
Consent only after you know what the procedure is intended to change, what it cannot change, and how success will be assessed. Vaginal appearance or diameter alone does not predict sexual function, which also depends on desire, arousal, lubrication, pain and pelvic-floor activity.
1. What benefit is realistic for my specific symptom? Ask whether the target is the vaginal canal, perineal scar, dryness, prolapse or appearance, and whether pelvic-floor physiotherapy or another treatment fits better.
2. What are the vaginal tightening risks? Request clear figures or ranges for bleeding, infection, scarring, narrowing, altered sensation, painful sex, pelvic-floor spasm, difficulty with penetration and problems during future examination or childbirth.
3. Could this affect a future pregnancy? Confirm whether to defer treatment, how pregnancy could change the repair, and whether vaginal birth could stretch or reopen it. There is no established evidence that tightening improves fertility.
4. What will recovery require? Get written timeframes for wound care, work, exercise, tampon use, intercourse and pregnancy planning; vaginal tissues heal over weeks, not overnight.
5. What is your plan if symptoms persist or worsen? Ask which examination findings support treatment and how urinary, bowel, prolapse and sexual symptoms will be followed.
A gynaecological consultation with Dr Bhavini Shah Balakrishnan should include childbirth injuries, medications, menopause or breastfeeding, prior pelvic surgery, future pregnancy plans, and assessment of the vulva, vaginal walls and pelvic-floor contraction and relaxation.
Related service
Cosmetic Gynecology Cosmetic gynecology is a field of medicine that focuses on the aesthetic and functional improvement of the female genitalia. View service → |
Frequently asked questions
What symptoms alongside vaginal laxity need medical assessment?
Pain, pelvic pressure, a vaginal bulge, changed bladder control, difficulty emptying the bladder, or bowel symptoms need assessment rather than self-diagnosis.
Why should the underlying cause be identified before vaginal tightening?
A looseness sensation can reflect pelvic-floor weakness, childbirth-related perineal injury, prolapse, hormonal tissue changes, or normal anatomy. Treatment should match the cause.
How do vaginoplasty, perineoplasty, laser, and radiofrequency differ?
Vaginoplasty is surgery involving the vaginal canal, while perineoplasty repairs or reshapes the perineum. Laser and radiofrequency are energy-based treatments that do not use the same surgical repair approach.
How does pelvic-floor physiotherapy compare with surgery and energy-based treatment?
Physiotherapy targets muscle strength, coordination, and relaxation without surgery. Surgery involves operative recovery, while energy-based treatment has different evidence, risks, and expected outcomes that require discussion.